Surface Anatomy of Beautiful Lower Eyelids
A mild bulge below the lashes, a gentle groove, a smooth transition from the lower eyelid to the cheek, no irregular bulges, no distinct grooves, no eyelid laxity, no eyelid malposition, good lash position.
There is a reason why lower eyelid blepharoplasty is considered to be the Rolls Royce of Plastic Surgery procedures: it requires bespoke assessment, bespoke planning, bespoke execution, and bespoke after-care. Much like a Rolls Royce. No two lower blepharoplasties are the same and there is a high risk of complications if any of these steps is not undertaken with great care. With lower blepharoplasty, nothing but the best will do.
What Procedure Do You Use for a Lower Blepharoplasty?
Whenever I lecture, plastic surgeons ask me this question. Patients ask the same question. The problem is that I use any mixture of all of these procedures, depending upon the analysis (see below) and surgery outcomes desired:
- Medial, central and lateral fat pocket reduction
- Fat transposition
- Fat grafts
- Orbito-malar ligament release
- Zygomatic ligament release
- Nasojugal groove correction
- Malar groove correction
- Lateral canthoplasty
- Lateral canthopexy
- Skin pinch technique
- Skin removal
- Oribularis sling
- Skin and orbicularis removal
- CO2 laser fractionated
- Erbium full strength or fractionated
- Chemical peel
- Tranconjunctival fat reduction and fat transposition (no external scars)
- Transcutaneous fat reduction and transposition (sub-ciliary incision)
- Medial canthopexy
- Asymmetric fat reduction
- Treatment of festoons
- Midface rejuvenation
- Treatment of crows’ feet
Including many of these procedures in a blepharoplasty still results in the procedure being called “Lower Blepharoplasty”! However, it is the details that make it a successful lower blepharoplasty with a natural-looking outcome.
The Multiplicity of Ways Lower Eyelids Age
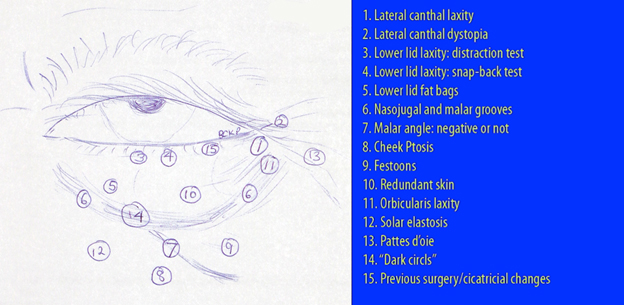 Assessment of the Aging Lower Eyelid:
Artist’s depiction of how we assess the different parts of the lower eyelid and surrounding areas.
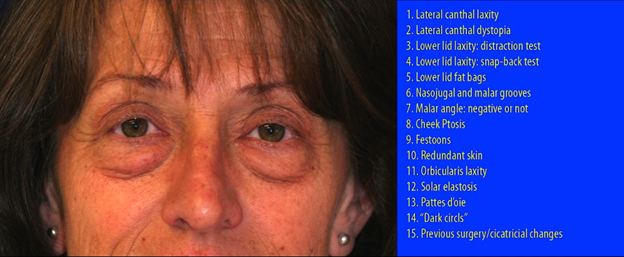 Assessment of the Aging Lower Eyelid:
These are just some of the factors we assess when addressing aging changes of the lower eyelids. Changes in skin collagen, actinic keratoses, fine wrinkles, pores, pigment, broken vessels and other factors are also considered and addressed. As can be seen, it is not just a case of “get rid of my bags,” as that would leave loose skin, worsened nasojugal and malar grooves and possibly malpositioned lower eyelids.
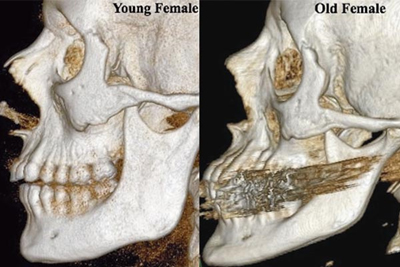 Aging of the Bones and How It Affects the Lower Eyelids:
Surgeons frequently forget to assess the aging of the facial bones. The malar bone regresses with loss of prominence and the opening of the orbit also increases in vertical and horizontal height. When severe, the bony changes need specific augmentation (with implants, tissue repositioning or tissue onlay grafting)
Relationship of the Lower Eyelids to Cheeks
Lower eyelids are often considered in isolation by plastic surgeons: do you want an upper blepharoplasty, a lower blepharoplasty, a brow lift, etc. However, the lower eyelids and cheeks have an intimate relationship and changes in the lower eyelids and cheeks often demands that both are addressed together to achieve a harmonious result.
Cheek ptosis, cheek volume loss, cheek irregularity, cheek fat pad reduction and cheek skin changes can all exacerbate the appearance of the lower eyelids.
 Aging of the Lower Eyelids and Cheeks:
the loss of volume in the cheeks, the cheek ptosis and atrophy of the skin all result in an exacerbation of the malar groove and nasojugal groove. This, in turn, makes the lower eyelid bags look worse and the medial, central and lateral fat pads can clearly be seen Furthermore, there is also atrophy of the skin and orbicularis muscle over the lower eyelids, resulting in thinning skin and more visible fat pads.
Compare the older photograph on the right to the younger photograph of the same patient on the left and you can see that the lower eyelid and cheek blend into one smooth curve. There are no distinct fat pads or eyelid bags visible, the cheeks are higher and the nasojugal and malar grooves are absent because of the fullness of the orbicularis, the high degree of collagen present in the lower eyelid skin, the cheek pad position, the cheek fullness and the firmness and fullness of the cheek skin. In such patients, we repair the lower eyelid with the cheeks (part of our Hammock Lift). The full Hammock Lift addresses the brows, the upper eyelids, the lower eyelids and the cheeks.
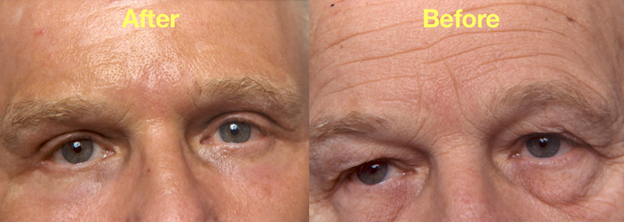 Before & After in a Male Who Underwent the Full Hammock Lift (Brows, Upper Eyelids, Lower Eyelids, and Cheeks).
Post-procedure is on the left and shows correction of the lower eyelid bulges, skin laxity, and lower eyelid laxity, along with correction of the nasojugal groove, correction of the malar groove, nano fatgrafts to the skin, laser to the skin, correction of the zygomatic groove, and rejuvenation of the lid-cheek junction with cheek repositioning.
 Aging Over 30 Years:
Concentrating on the lower eyelids, there are fat bags, nasojugal grooves, malar grooves, cheek ptosis, fat atrophy, cheek volume loss, skin collagen loss, and most importantly, marked festoons. Festoons are collections of fluid in loose skin over the malar eminence and are very difficult to treat in isolation. We address the lower eyelids, festoons, and cheeks as one, as shown below.
 Lower Blepharoplasty and Cheek Lifts with Volume Augmentation and Treatment of Fat, Skin, Grooves, Fat pads, etc:
This allows the lower eyelids to look fuller without the fat bags, recreates a smoother curve from the lower eyelids to the cheeks, improves the nasojugal grooves and the malar grooves, creates fuller cheeks (without creating the chipmunk cheeks one often sees), and improves the festoons immensely. The exact techniques we use to treat festoons are discussed in a different article.
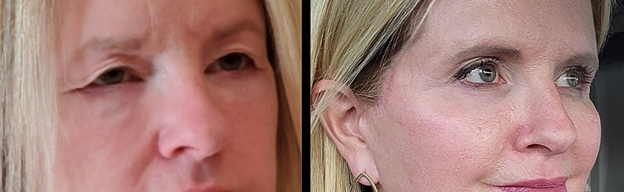 Another Example of the Hammock Lift:
The brows were repositioned, the upper eyelid hooding and fullness were treated without creating hollows in the upper eyelids, the lower eyelid bags were improved, the cheeks were repositioned and augmented with fat grafts, and the skin was treated with the laser and stem cells. This gives a very youthful result without any hallmarks of surgery having been done.
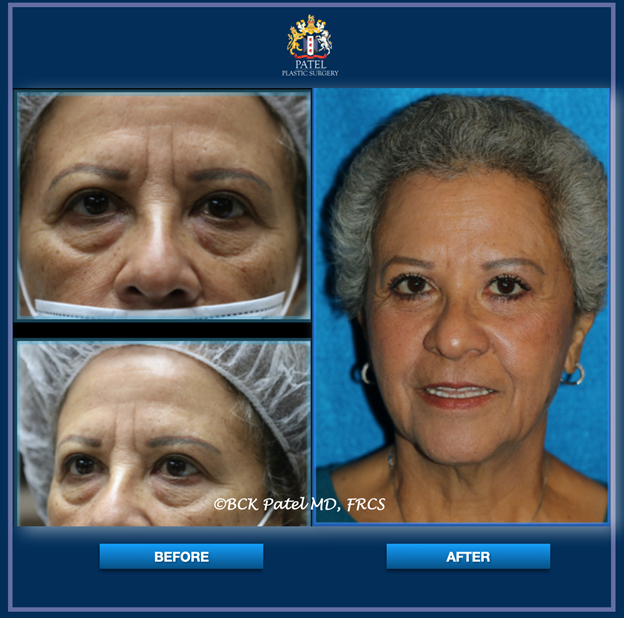 Before & After in a Latina Female:
Sex, age, race, lifestyle, occupation and whether in the public eye (on television, on camera, etc) must all be considered when planning lower blepharoplasty. We always take racial characteristics into account. In a Latina face, the lower eyelids develop fullness (eyelid bags) early, but wrinkles and fat atrophy occur much later. In this patient, we repositioned her cheeks and improved the lower eyelid bags with some fat removal and fat repositioning together with skin tightening. The patient has no makeup in any of the before or after photographs. The lazy lower eyelids were repositioned (“tightened”), as Latina faces look more attractive with firm and slightly upward-slanting lower eyelids. Fat was also grafted into the deep frown lines (the “elevens”), so her brows and frown lines also appear better. Also, note the improvement in the “fat nose” at the base of the nose. We always slim the bridge of the nose when we are working anywhere near the nose and brows and fill any wrinkles, as it avoids the need for repeated fillers.
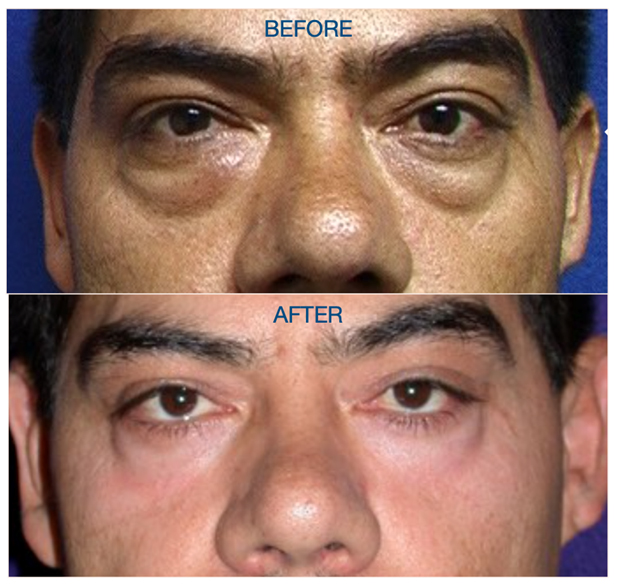 Before & After in a Latina Male:
In Latina males, lower eyelid bags appear early, but wrinkles show up later. Furthermore, they generally do not develop festoons, but the nasojugal groove and the malar groove do deepen early. Here, we reposition the fat to fill the grooves and reduce the lower eyelid fullness using our transconjunctival lower blepharoplasty approach, which avoids visible lower eyelid scars, as such scars in Latina males can result in pigmentation. With small lateral canthal incisions, the lower eyelids are tightened (canthoplasty and canthopexy) and the skin is treated with a chemical peel. In this patient, the whole face was treated so the nose pores and skin as well as the face and eyelid and cheek skin look better. Individualized surgery for specific problems in different races.
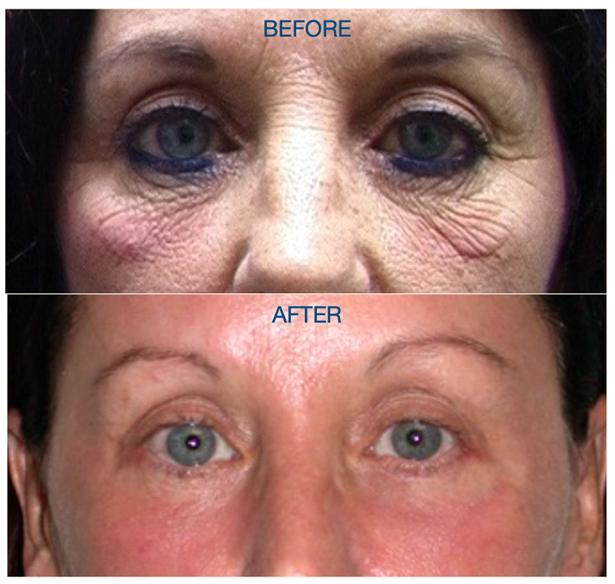 Before & After in a Caucasian with Fitzpatrick Type 3 Skin:
Here, there was no real fat prolapse but some lower eyelid laxity and much atrophy of the skin with repeated previous attacks of allergies causing skin laxity and multiple wrinkles and enlarged pores. We tightened the lower eyelids, tightened the skin, and used extensive lasers and injection of mesenchymal stem cells and nano fat grafts to get smoother skin. Note that the lower eyelids and cheek skin now looks congruous and more youthful. Fat grafts were also used to create fullness in the cheeks and temples and the crow’s feet were improved with lasers and nano fat grafts. An individualized approach to a unique kind of lower eyelid aging.
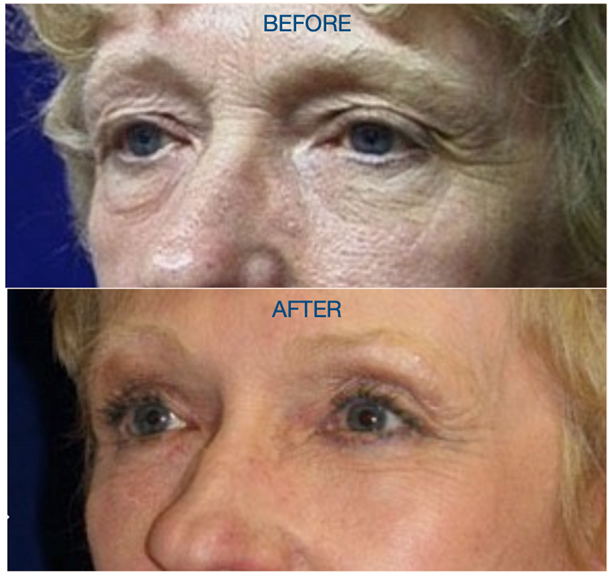 The Power of the Hammock Lift in a Patient with Fitzpatrick Type 1 Skin:
This lady wanted “an upper and lower blepharoplasty,” but what we performed was the Hammock Lift, including a brow lift, upper blepharoplasty, lower blepharoplasty, cheek lift, attenuation of the frown muscles, nano fat grafts to the forehead, brows, cheeks and malar groove, CO2 fractionated laser, and and mesenchymal stem cells to improve the skin immensely. She looks fresh (less tired), with a very natural result and no tell-tale signs of surgery.
Schedule a Lower Blepharoplasty Consultation in Salt Lake City
We can arrange a physical clinic appointment or a Zoom appointment as we see patients from all over the country and from overseas. Schedule your visit
using our online form or by calling Dr. Patel’s office at (801) 413-3599 for Salt Lake City patients or (435) 215-0014 for Saint George patients.
References:
- Patel B.C.K., Anderson R.L. Transconjunctival blepharoplasty. Plast Reconstr Surg. 1996;97:1514.
- Patel B.C.K., Patipa M., Anderson R.L., McLeish W. Management of postblepharoplasty lower eyelid retraction with hard palate grafts and lateral tarsal strip. Plast Reconstr Surg. 1997;99:1251–1260.
- Patel BCK, Malhotra R. Transconjunctival blepharoplasty. StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing;2020 Aug 24. PMID: 30844179
- Patel B.C.K., Anderson R.L. Naugle T.C., eds. Blepharoplasty: a systematic approach. Diagnosis and Management of Oculoplastic and Orbital Disorders. Kugler Publications, Amsterdam/New York;1996:59–78.
- Joos Z, Patel BC. Analysis of the aging Indian Face: the first comparative anthropological study. Journal of the Tamil Nadu Ophthalmic Association (JTNOA). 2017 55(2); 972–980




